预约演示
更新于:2026-11-08

Medtronic Plc
更新于:2026-11-08
概览
标签
心血管疾病
非降解型分子胶
重组多肽
疾病领域得分
一眼洞穿机构专注的疾病领域

技术平台
公司药物应用最多的技术
靶点
公司最常开发的靶点
关联
靶点 |
作用机制 |
在研机构 |
原研机构 |
在研适应症 |
非在研适应症 |
最高研发阶段 |
首次获批国家/地区 |
首次获批日期 |


靶点 |
作用机制 |
在研机构 |
原研机构 |
在研适应症 |
非在研适应症 |
最高研发阶段 |
首次获批国家/地区 |
首次获批日期 |
靶点 |
作用机制 |
在研机构 |
原研机构 |
在研适应症 |
非在研适应症 |
最高研发阶段 |
首次获批国家/地区 |
首次获批日期 |


NCT06606054
WSO - The Brain and hEart globAl iniTiative (BEAT) Stroke

NCT07901049
A Prospective, Multi-center, Single-arm, Post-market Study of the Medtronic Hugo™ Robotic-Assisted Surgery (RAS) System in Urologic Surgery
NCT07748962
Decoding the Neural Mechanisms Underlying Postural Instability and Gait Dysfunction in Parkinson's Disease

100 项与 Medtronic Plc 相关的临床结果
登录后查看更多信息
登录后查看更多信息
2026-12-01JOURNAL OF VASCULAR AND INTERVENTIONAL RADIOLOGY
Real-World Safety and Performance of Nylon and PGLA Fibered Detachable Coils in Peripheral Embolization: A Prospective Multicenter Registry
Article
作者: Makary, Mina S ; Elsaadany, Amr ; Tarter, Wyatt ; Wu, Vincent ; Shrestha, Prashant
PURPOSE:
To evaluate the safety and effectiveness of the Concerto nylon and PGLA fibered detachable coil system (Concerto, Medtronic, Minneapolis, MN) for peripheral embolization in the Product Surveillance Registry (NCT01524276).
MATERIALS AND METHODS:
A prospective, multicenter, global observational registry enrolled patients undergoing arterial or venous embolization with the fibered detachable coil system. Patients were grouped by disease state and followed for up to 12 months. Primary safety and performance outcomes included technical and clinical success at index procedure, nontarget tissue ischemia or nontarget embolization, secondary embolization of target lesion, coil compaction, device fracture, and target lesion occlusion at follow up. Secondary objectives were a subanalysis of pain scores based on the visual analog scale (VAS) and Patient Global Impression of Change (PGI-C) among patients with pelvic venous disorder (PeVD).
RESULTS:
130 patients were enrolled across 13 sites. Technical success was achieved for 97.8% of coils (613/627; 95% CI, 96.3-98.8), and clinical success was achieved for 97.0% of target lesions (161/166; 95% CI, 93.1-99.0). No nontarget tissue ischemia, nontarget embolization, secondary embolization, or device fracture occurred. Coil compaction occurred in 0.3% of coils (2/627). Target lesion occlusion rate was 100% at 12 months. A subanalysis of the PeVD cohort demonstrated a reduction in VAS pain scores. PGI-C was improved overall from the 30-day follow-up to the 12-month follow-up.
CONCLUSIONS:
The fibered detachable coil system demonstrated safe and effective performance across multiple peripheral vascular embolization disease states in real-world clinical practice.
2026-11-03Journal of the American Heart Association
Evaluation of Acute Electrical and Hemodynamic Improvement During Left Bundle‐Branch Area Pacing Modalities for Resynchronization Therapy
Article
作者: Liang, Yixiu ; Yu, Ziqing ; Su, Yanling ; Li, Minghui ; Su, Yangang ; Whinnett, Zachary I. ; Xiao, Zilong ; Li, Xiao ; Pan, Lei ; Lu, Hongyang ; Arnold, Ahran D. ; Chen, Juecheng
Background:
While cardiac resynchronization therapy is effective in dyssynchronous heart failure, suboptimal response remains frequent. The acute hemodynamic profile of different left bundle‐branch (LBB) area pacing modalities is poorly defined. Moreover, atrioventricular optimization guided by QRS duration (QRSd) may not yield the greatest hemodynamic benefit.
Methods:
Twenty‐four patients with heart failure, reduced ejection fraction, and LBB block underwent sequential testing of right ventricular septal pacing, left ventricular septal pacing, nonselective LBB pacing, and selective LBB pacing during cardiac resynchronization therapy implantation in a prospective, within‐subject physiological study. At each modality, electrical end points were QRSd and vectorcardiographic QRS area; hemodynamics were assessed with beat‐to‐beat systolic blood pressure (SBP). The atrioventricular interval producing maximal SBP improvement was compared with that producing the narrowest QRSd.
Results:
LBB area pacing
modalities significantly reduced
QRSd
, compared with right ventricular septal pacing (nonselective
LBB pacing,
114.0±16.8 milliseconds; selective
LBB pacing
, 118.4±14.1 milliseconds; left ventricular septal pacing, 124.6±16.0 milliseconds; right ventricular septal pacing, 144.4±27.6 milliseconds; all
P
<0.01). At the
atrioventricular
interval that produced maximized
SBP
improvement,
QRSd
remained narrower with
LBB area pacing
than right ventricular septal pacing, and selective
LBB pacing
provided the greatest hemodynamic improvement (
ΔSBP
16.3±5.2
mm Hg
), exceeding left ventricular septal pacing (13.5±6.2
mm Hg
) and nonselective
LBB pacing
(12.8±6.3
mm Hg
; all
P
<0.05). Across modalities, the
atrioventricular
interval that maximized
ΔSBP
was consistently shorter than that minimizing
QRSd
(mean difference, 18–29 milliseconds).
Conclusions:
Selective LBB pacing yields the greatest acute hemodynamic benefit, and the hemodynamic‐optimal atrioventricular interval is shorter than the electrical‐optimal atrioventricular interval, suggesting that modest atrioventricular interval shortening after electrical optimization may better maximize hemodynamics.
Registration:
URL:
https://www.clinicaltrials.gov
; Unique Identifier: NCT07032064.
2026-10-01HEART RHYTHM
Safety and performance of a novel defibrillation lead for left bundle branch area placement: Primary results of the LEADR LBBAP clinical trial
Article
作者: Zakaib, John S ; Vijayaraman, Pugazhendhi ; Afzal, Muhammad R ; Schloss, Edward J ; Geelen, Tessa ; Mason, Pamela K ; Denman, Russell ; Platner, Megan L ; Pokharel, Parash ; Whinnett, Zachary I ; Tanner, Jocelyn ; Burrell, James ; Jastrzębski, Marek ; Liu, Xingbin ; Crossley, George H ; Abhayaratna, Walter P ; Philippon, François ; Kron, Jordana ; Butler, Kiah
BACKGROUND:
Right ventricular placement of the OmniaSecure defibrillation lead has demonstrated high defibrillation success and low occurrence of lead-related major complications. With the advent of left bundle branch area pacing (LBBAP) as a physiological pacing option, the use of the OmniaSecure lead may be a viable alternative for LBBAP in the implantable cardioverter-defibrillator population.
OBJECTIVE:
This study aimed to understand the defibrillation efficacy at implant and the safety of the OmniaSecure lead for LBBAP.
METHODS:
The global Lead Evaluation for Defibrillation and Reliability LBBAP trial enrolled patients indicated for de novo implantation of a primary or secondary prevention implantable cardioverter-defibrillator or cardiac resynchronization therapy with a defibrillator. Per study protocol, LBBAP includes electrocardiographic characterization of left bundle branch pacing and deep septal pacing. The primary efficacy objective was defibrillation efficacy at implant exceeding a prespecified threshold of 88% in ≥160 patients. The primary safety endpoint was to demonstrate the OmniaSecure lead-related major complication rate at 3 months after implant.
RESULTS:
A total of 307 patients underwent an LBBAP implant attempt (age 64.9 ± 12.2 years; 28.7% female; body mass index 28.4 ± 6.1 kg/m2). A total of 293 patients were successfully implanted per protocol (95.4%). The primary efficacy objective was met with 100% of patients defibrillated to protocol. The observed freedom from OmniaSecure lead-related major complications at 3 months was 97.9% (95% confidence interval 95.8-100). There were zero study lead fractures, no oversensing adverse events, and stable electrical parameters through 2.6 ± 2.5 months' follow-up.
CONCLUSION:
These results demonstrate that implantation of OmniaSecure lead when intended for LBBAP results in high defibrillation success at implant, stable short-term electrical parameters, and a low rate of OmniaSecure lead-related major complications at 3 months.
100 项与 Medtronic Plc 相关的药物交易
登录后查看更多信息
100 项与 Medtronic Plc 相关的转化医学
登录后查看更多信息
组织架构
使用我们的机构树数据加速您的研究。
登录
或

管线布局
2026年11月10日管线快照
管线布局中药物为当前组织机构及其子机构作为药物机构进行统计,早期临床1期并入临床1期,临床1/2期并入临床2期,临床2/3期并入临床3期
临床2期
1
4
批准上市
其他
10
登录后查看更多信息
当前项目
登录后查看更多信息
药物交易
使用我们的药物交易数据加速您的研究。
登录
或
转化医学
使用我们的转化医学数据加速您的研究。
登录
或
营收
使用 Synapse 探索超过 36 万个组织的财务状况。
登录
或
科研基金(NIH)
访问超过 200 万项资助和基金信息,以提升您的研究之旅。
登录
或
投资
深入了解从初创企业到成熟企业的最新公司投资动态。
登录
或
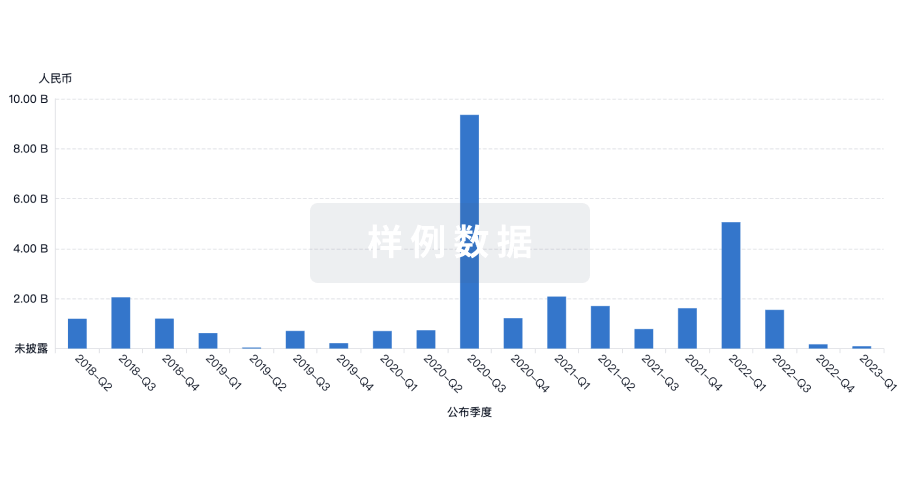
融资
发掘融资趋势以验证和推进您的投资机会。
登录
或
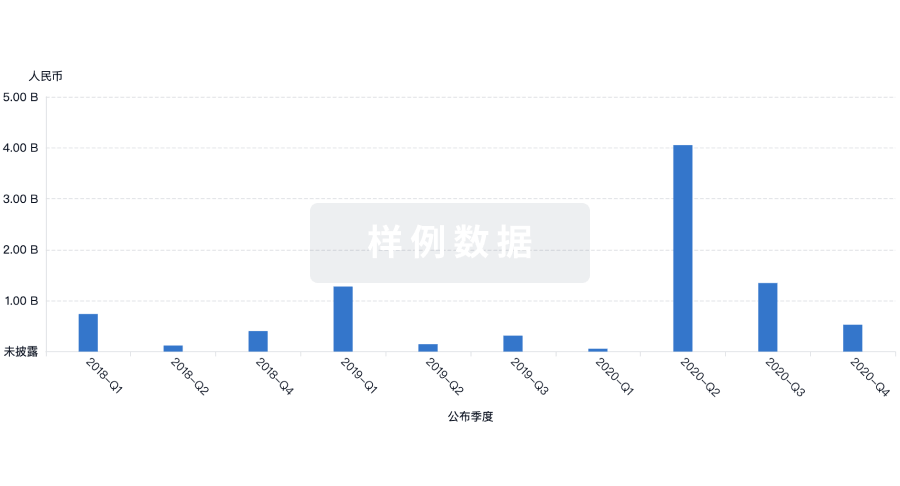
提出任何生物医药研究问题
让每一步生物医药决策都精准制胜
基于十亿级生物数据与全球情报的精准 AI,赋能早期药物发现
立即开始免费试用!
智慧芽新药情报库是智慧芽专为生命科学人士构建的基于AI的创新药情报平台,助您全方位提升您的研发与决策效率。
立即接入生物医药数据包
智慧芽新药库数据也通过智慧芽开放平台,以MCP或API服务形式对外开放。立即使用我们的MCP服务定制您的LLM智能体。
生物序列数据库
生物药研发创新
免费使用
化学结构数据库
小分子化药研发创新
免费使用